Can Chronic Pain Go Away? What Actually Decides Whether Pain Changes

Can chronic pain go away? For many people, persistent pain can change substantially, even after years, because the neurologic sensitivity that keeps most chronic pain going is changeable. I can't honestly promise anyone a life without pain, and nobody who is being straight with you can either. But "will my pain ever go away?" and "can my pain get better?" are two different questions, and the second one has a far more hopeful answer than most people are ever given.
If you've been told "this is something you'll have to live with," that sentence deserves a second look. Here is what actually decides whether pain changes, and why how long you've had it is not the deciding factor.
Why "Does Chronic Pain Last Forever?" Is the Wrong Question to Stop At
When someone asks me whether chronic pain lasts forever, they are usually asking two things at once. The first is a question about a cure: will this ever be completely gone? The second is a question about direction: can anything in my life get better from here?
Those questions get collapsed together, usually in a doctor's office. A clinician says "there's no cure," and the person hears "nothing will change."
"No cure" is a prognosis. It is not a treatment plan. A prognosis tells you what someone expects to happen. A plan tells you what to do next. Plenty of people leave with the first and none of the second, and assume the absence of a plan means the absence of possibility.
"There's nothing more we can do" is not an evidence-based statement. It describes the limits of the approaches one clinic offers. It says nothing about the limits of your biology.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
Why Chronic Pain Sticks Around After the Tissue Heals
Most persistent pain starts with something physical: an injury, a surgery, a strain. Tissues have a healing timeline, and in most cases it runs its course. The pain keeps going anyway.
The reason is that pain isn't produced by tissue alone. It is produced by a signaling system: the nerves and pathways that detect, transmit, process, and respond to information from the body. When pain persists, that system often becomes more sensitive and more reactive. I call this neurologic sensitivity. Overactive pain pathways start responding to input that shouldn't be threatening. The brain's map of the painful area can become smudged, so signals get blurred and misread. Protective responses like guarding, bracing, and avoiding movement stay switched on long after they're useful.
This is why so many people hear "your scans look fine" and still hurt. The scan is looking at structure. Neurologic sensitivity is a change in how the system functions, and it doesn't show up on an MRI. I explain this pattern in more depth in why chronic pain persists after treatment.
Here is the part that matters most for the question you came here with. A system that adapted in one direction can adapt again. Neurologic pathways respond to the input they receive. That capacity doesn't expire after a certain number of years, and it doesn't disappear because a diagnosis was given.
What Decides Whether Chronic Pain Can Change
If neurologic sensitivity is changeable, why doesn't everyone improve? Because change depends on several factors, and standard care usually addresses one or two.
Whether the actual driver has been identified
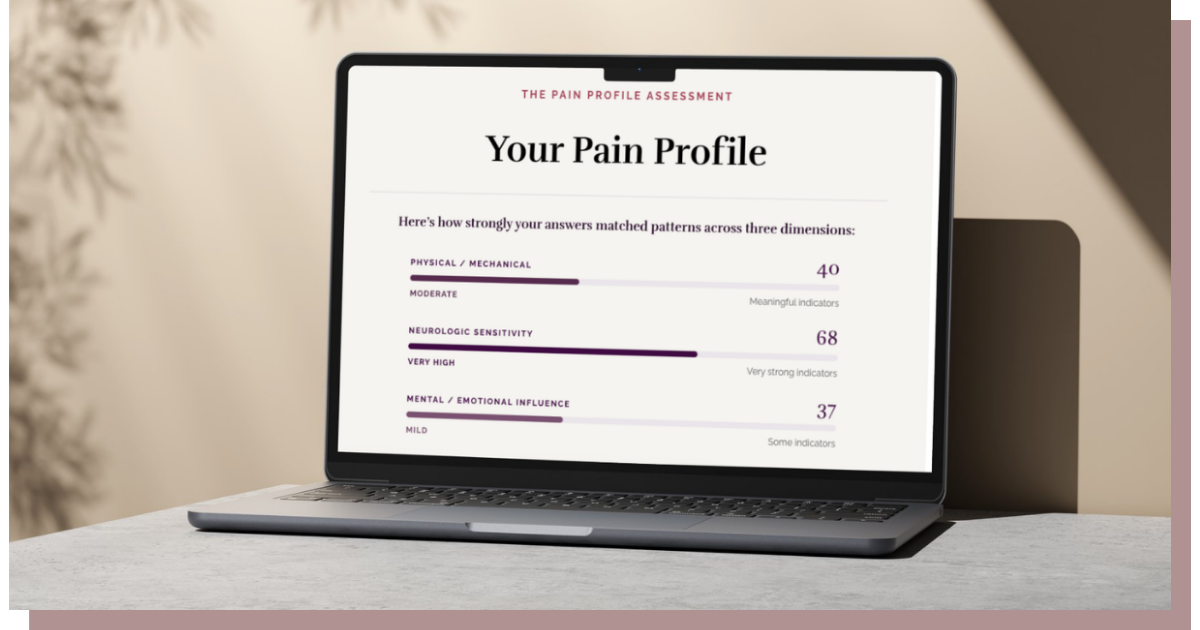
Persistent pain has more than one dimension. There is the physical side: tissues, joints, strength, mobility. There is neurologic sensitivity. And there is the mental and emotional load that comes with living in pain. When the main driver is neurologic sensitivity and the treatment plan is aimed only at the tissue, results stall. Most programs start with strengthening. That's exactly why they stall.
Whether amplifiers are being addressed
Poor sleep, ongoing stress, fear of movement, and repeated flare-ups act as amplifiers that keep sensitivity elevated. Reducing them is necessary but not sufficient: calming things down doesn't teach an overactive system to process input accurately again.
Whether the work happens in the right order and at the right dose
Order and dose decide whether an approach helps or flares you. A reactive system that gets pushed too hard learns to react harder. A system that gets no challenge at all stays exactly where it is. The principle I build everything around is simple: push to it, not through it.
Whether you have a process instead of a list
Many people with long-standing pain have tried injections, medications, supplements, gadgets, and therapies found online, each one layered on the last and judged by whether it fixed everything. That is the Singular Fix at work: the belief that one treatment should solve a problem with several moving parts. A process introduces the right pieces in sequence, so you can tell what's helping and build on it.
What "Better" Can Look Like
I want to be clear about what improvement means, because it's often bigger than a number on a pain scale.
When neurologic sensitivity is treated directly, I regularly see lives open back up. Activity tolerance grows. Flares become less frequent and less frightening. Sleep improves. Fear loosens its grip on movement. Many people reach days with little or no pain, something they had stopped believing was possible.
Some people still have hard days. That doesn't cancel out the rest. If "better" only means "permanently gone," most people will feel they've failed. If "better" means walking the dog, getting back to work, sitting through church without planning an exit, that change is realistic for far more people than are ever told so.
Between Giving Up and Burning Out
When pain goes on for a long time, people tend to drift toward one of two ends of a spectrum.
On one end is over-acceptance. Life shrinks to fit around the pain, and the story becomes "this is just the way it is now" or "I've tried everything and there's nothing more we can do." On the other end is over-striving: constant researching, jumping from one approach to the next, pouring every ounce of energy into finding the answer until the search itself causes burnout.
Both responses make sense. Acceptance protects you from more disappointment. Hope drives people to keep looking for answers, and ultimately to find them. Unchecked, either one keeps you stuck: too much acceptance and you settle; too much hope without direction and you end up on a hamster wheel.
The place where progress happens sits in between. Accept where things are today, without accepting that they have to stay this way. Then move forward with clear steps in the right order, one chapter at a time.
Many of the women I work with waited a long time for the next scan, the next specialist, the perfect moment, because waiting felt safer than risking another disappointment. The people who get their lives back are not the ones who wait for certainty. You don't need a scan to give you permission to start.
One caveat: if your pain is new, changing quickly, or comes with symptoms that haven't been evaluated, talk to your doctor to rule out other causes first.
So, Will Your Chronic Pain Ever Go Away?
I can't tell you your pain will disappear. I can tell you that "you'll always have pain" is far less certain than it sounds, and that "nothing can change" is not supported by what we know about how the signaling system works. Neurologic sensitivity is changeable. Time alone doesn't decide your outcome. What decides it is whether the right driver is being addressed, in the right order, at a dose your system can tolerate.
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.