Chronic Pain Treatment Options: The 4 Types of Treatment and the One Most People Never Try

Chronic pain treatment options fall into four categories: treatments that reduce pain intensity, treatments that fix structure and mechanics, mind-body treatments that address stress and emotions, and neurologic treatments that target the sensitivity of the pain system itself. Most people with persistent pain have tried plenty from the first three. Very few have been offered the fourth, and it's often the missing piece.
If you feel like you've tried everything, sorting your list into these categories turns a pile of failed treatments into a map of what has been covered and what hasn't.
Why the Category Matters More Than the Treatment
Every pain treatment is designed to solve a specific part of the pain problem. When one fails, it usually isn't because it was a bad treatment. It was aimed at a part of the problem that wasn't the main driver.
Ten treatments from the same category is not ten different attempts. It's the same attempt repeated. That's why people can spend years and thousands of dollars without lasting change, and then conclude nothing works.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
Category 1: Treatments That Reduce Pain Intensity
These reduce or mask how much pain you feel in the moment. They include:
- Medications, including NSAIDs, opioids, and nerve pain medications
- Injections, nerve blocks, and ablations
- TENS units and electrical stimulation
- Heat and ice
Managing pain intensity matters, and these have a place. They address the symptom, though, not what keeps producing it. When the effect wears off, the pain returns. In some people, the system even adapts to these treatments and becomes more reactive to compensate. Any change to medications or procedures is a conversation for your doctor.
Category 2: Treatments That Fix Structure and Mechanics
These aim to correct what's physically wrong with muscles, joints, discs, alignment, or movement patterns:
- Physical therapy focused on strength and mobility
- Chiropractic care
- Massage
- Surgery
- Weight loss
Picture a bedroom light that won't turn on. You try five different bulbs and nothing changes. At some point you realize the bulb was never the problem; the trouble is in the circuit. Structural treatments address the bulb. When several of them haven't produced lasting relief, that's important information. Structure alone isn't what's keeping the pain going.
Category 3: Mind-Body Treatments
These address the mental and emotional side of pain and the body's stress response:
- Meditation and mindfulness
- CBT, EMDR, and trauma therapy
- Journaling, grounding, and tapping
- Biofeedback and breathing practices
- Pain Reprocessing Therapy (PRT) and similar programs
- Vagus nerve techniques
There's real value here. Mood, stress, and emotion influence pain, and reducing those amplifiers helps.
There's also a trap. Some approaches claim that all chronic pain is a mind-body problem, and that resolving your emotions or stress response will resolve the pain. That oversimplifies it. Pain isn't purely a thinking problem. Mind-body work is one important piece, and it doesn't address structural factors or the neurologic changes that keep persistent pain going.
Category 4: Neurologic Treatment
This is the category most people with complex or persistent pain have never tried. That's not because they weren't diligent. The medical system rarely offers it.
Persistent pain is driven in part by neurologic adaptations that increase sensitivity. These are real, measurable changes in the peripheral nerves, the spinal cord, and the brain. They make the system more reactive, amplify pain, and keep protective responses firing regardless of what's happening in the tissue.
A neurologic approach targets those changes directly. It brings together:
- Pain Neuroscience Education (PNE), so the pain stops reading as an emergency and the uncertainty that keeps the alarm on starts to lift
- The Graded Motor Imagery (GMI) sequence, to sharpen smudged body maps in the brain
- Sensory discrimination, to restore accurate processing of touch and other input
- Neurodynamic techniques, to address peripheral nerves that have become overactive
- Pacing adapted for hypersensitivity, so activity builds tolerance instead of flares: push to it, not through it
Each method targets a different level of the nervous system. Together they address the part of the problem the other three categories don't touch, which is why this approach can work after everything else hasn't. It also goes deeper than managing the stress response, because it targets the reason that response keeps firing so easily. I explain more in why neurologic rehab is not mindset work.
Why Order Matters as Much as Category
Even inside the neurologic category, the sequence decides the outcome. Strengthening and stretching matter, and most people with persistent pain have real deconditioning. When sensitivity is still high, though, exercise often backfires. The nervous system guards the area, the right muscles don't engage, and pain spikes after every session. Most programs start with strengthening. That's exactly why they stall.
The same methods help or flare depending on when they're introduced and at what dose. Understanding comes first, then the conditions that lower the load on the system, then building tolerance for activity, then directly reducing sensitivity, and finally rebuilding strength on a steadier foundation. Picking one piece off that list rarely works, because a complex problem doesn't respond to a singular fix.
What Your List of Failed Treatments Is Telling You
If most of what you've tried falls into categories 1, 2, and 3, with nothing from category 4, that list isn't a record of failure. It's a map pointing to what's been missing.
The standard of care for complex pain is sub-standard care, and that isn't your fault. You've been working with the options you were given. There's a whole category you haven't tried yet.
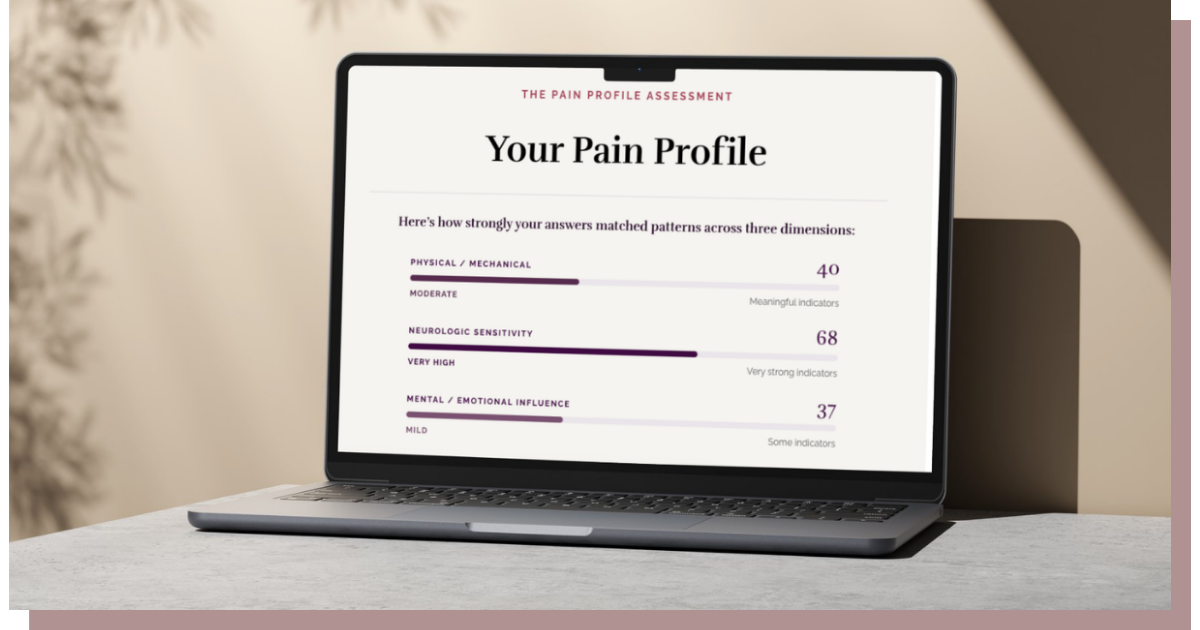
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.