Chronic Widespread Pain vs. Fibromyalgia: What's the Difference?
Chronic widespread pain and fibromyalgia overlap, but they are not the same thing. Chronic widespread pain describes a pain pattern: persistent pain spread across multiple regions of the body. Fibromyalgia is a diagnosis with its own criteria, which pairs widespread pain with a wider cluster of symptoms such as fatigue, unrefreshing sleep, and cognitive symptoms often described as brain fog.
So everyone with fibromyalgia has widespread pain, but not everyone with widespread pain has fibromyalgia. Underneath both, there is often a shared layer that responds to treatment: neurologic sensitivity. Here is how the two terms differ, why the difference matters, and what to do with it.
Chronic Widespread Pain: A Description of the Pattern
Chronic widespread pain is a descriptive term. It tells you where the pain is and how long it has been there. Pain shows up in several areas of the body, often on both sides and above and below the waist, and it persists for months rather than days or weeks.
What the term does not tell you is why. Widespread pain can come from a long list of sources. Some are inflammatory or autoimmune. Some are metabolic or hormonal. Some relate to medications. And many involve a signaling system that has become more sensitive over time. Because the list is long, the first step is a medical evaluation. If you have widespread pain, talk to your doctor to rule out other causes before settling on any explanation.
Some people stay in this category for years. Their pain is real and widespread, their tests come back normal, and their symptoms do not fit neatly into a named condition. They are left holding a question mark instead of a diagnosis.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
Fibromyalgia: A Diagnosis With Its Own Criteria
Fibromyalgia is a specific diagnosis. Widespread pain is part of it, but the criteria also look at the broader picture: how severe the symptoms are and whether pain comes with fatigue, sleep that does not restore you, and changes in memory and concentration. A physician makes the diagnosis after considering other conditions that could explain the symptoms.
That broader symptom cluster is the main difference. Two people can have the same map of pain across their body. One has significant fatigue, poor sleep, and brain fog alongside it and meets the criteria for fibromyalgia. The other has the pain without the rest of the cluster and is described as having chronic widespread pain.
A diagnosis can be valuable. It can put a name to something that has been dismissed for years and open doors to care. It can also become a closed file. Once fibromyalgia sits at the top of a chart, new symptoms tend to get attributed to it without a second look. A new symptom deserves its own evaluation, whatever label is already in your record.
The Shared Layer Underneath
Whichever term fits you, there is often a common layer underneath: neurologic sensitivity. When pain persists, the signaling system adapts. Pain pathways that fire often become overactive. The protective response stays switched on long after the original reason for it has passed. The brain's map of the body can become smudged, so ordinary input gets read as a threat.
Those adaptations can concentrate in one area or spread across the body. When they spread, the result can look like chronic widespread pain. When they come with fatigue, sleep disruption, and cognitive symptoms, the pattern may earn a fibromyalgia diagnosis. This is the same principle I use when explaining fibromyalgia and CRPS: different diagnoses, with a shared layer of sensitivity that responds to the same principles.
A shared layer does not make the conditions identical. Fibromyalgia, chronic widespread pain from other causes, and CRPS each deserve to be assessed on their own terms. The point is narrower and more useful: the sensitivity layer, wherever it shows up, is treatable.
Why the Distinction Matters for Treatment
The label shapes the conversation. A fibromyalgia diagnosis often leads to a symptom-by-symptom plan: something for sleep, something for fatigue, something for the pain. A chronic widespread pain description often leads to more testing, and when the tests are normal, to very little at all.
Both routes can miss the same thing. When you treat a label, you get a list of symptoms to manage one at a time. When you address the mechanism, you work on the sensitivity that is producing many of those symptoms in the first place. That is a very different plan.
Addressing neurologic sensitivity draws on evidence-based methods: pain neuroscience education, the Graded Motor Imagery sequence, sensory discrimination, neurodynamic techniques, pacing adapted for a sensitive system, and progressive strengthening once sensitivity settles. What decides whether those methods help or flare you is the dose, the order, and how they are adjusted to the person. That holds whether your chart says fibromyalgia, chronic widespread pain, or nothing at all.
I go deeper into why so many persistent pain conditions share this layer in what chronic pain conditions have in common.
Questions Worth Asking Your Doctor
If you are trying to work out which term fits you, a few questions can make your next appointment more productive:
- Have the other causes of widespread pain been ruled out, and which ones were checked?
- Do my fatigue, sleep, and cognitive symptoms fit the fibromyalgia criteria, or is my pain the main feature?
- If a new symptom appears, how will we decide whether it needs its own workup?
- Beyond managing symptoms, what is the plan for the sensitivity driving them?
The answer to the last question is often thin. That gap is where most people with widespread pain get stuck, and it is the part of the picture that can change.
Your Label Is a Starting Point
Chronic widespread pain and fibromyalgia describe real experiences. One names a pattern. The other names a diagnosis with a broader set of symptoms. Neither label, on its own, tells you what is driving the pain or what to do next.
The question worth asking is the same in both cases: what is actually driving this pain, and what does it respond to? When neurologic sensitivity is part of the answer, there is a clear path forward.
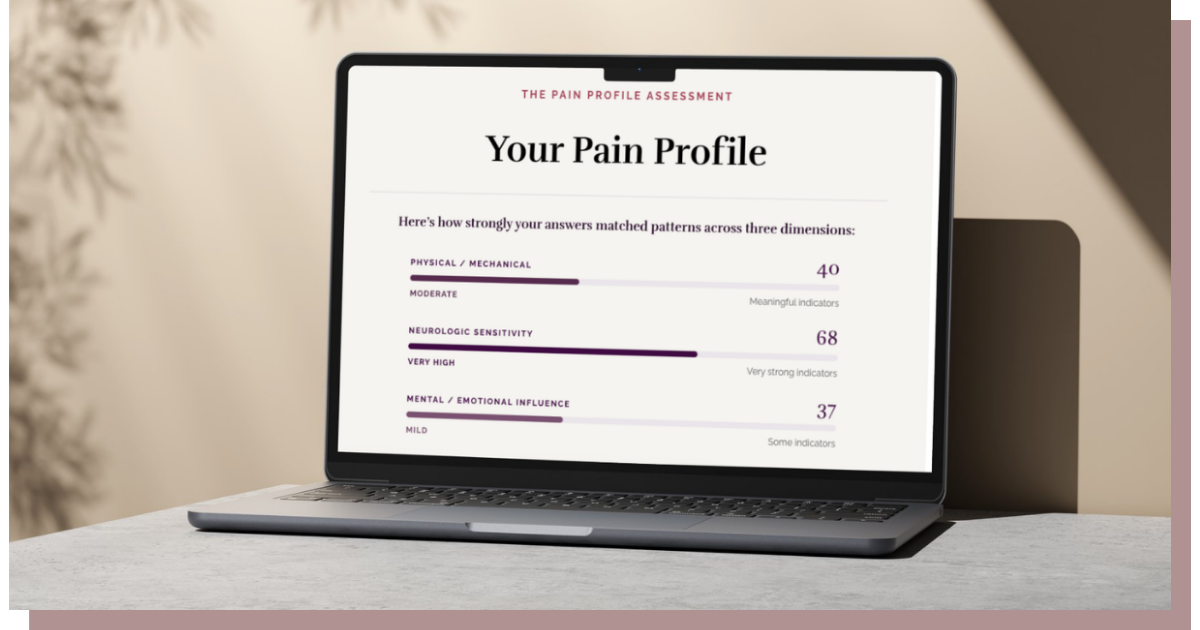
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.