Why Didn't My Epidural Steroid Injection Work? What a Failed Injection Tells You
An epidural steroid injection is designed to reduce inflammation around an irritated nerve root. If yours didn't help, or helped for a few weeks and then wore off, that result is useful information: inflammation at that nerve root may not be the main thing driving your pain. In persistent pain, overactive pain pathways often are, and an injection isn't built to reach them.
That's an important distinction, because a failed injection usually gets framed as a dead end. It's better understood as a clue about where to look next.
What an Epidural Steroid Injection Is Designed to Do
An epidural steroid injection places a corticosteroid, often along with a numbing medication, into the space around the spinal nerve roots. Corticosteroids are anti-inflammatory. The goal is to reduce swelling and chemical irritation around a nerve root that's being aggravated, commonly by a disc herniation or narrowing in the spine, so that the nerve becomes less irritated and the pain it produces settles.
Notice what that target is: local inflammation at a specific spot. The injection doesn't change the disc, the joint, or the bone. And it doesn't change how your signaling system processes pain signals once they leave that spot.
When local inflammation is the main driver, that targeted approach can work well. The question is what happens when it isn't.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
Why an Injection Might Not Work, or Wear Off
There are practical, procedural reasons an injection can fall short, and those belong in a conversation with the physician who performed it. Talk to your doctor to rule out other causes and to understand what they were targeting.
There's also a reason that rarely gets explained to patients: the pain may be coming less from the inflamed nerve root and more from the way the nervous system has adapted to months or years of pain.
When pain persists, the nerves and pathways that carry and process pain signals change. They become more responsive, react to more things, and stay activated longer than they used to. That's neurologic sensitivity. In a sensitive system, the signal is amplified along the way, well beyond the original site. Reducing inflammation at the nerve root lowers one input, but the amplification is still running.
That explains a few patterns I hear about constantly:
- An injection that helps a little, but not nearly as much as expected.
- Relief that lasts a short window and then returns to baseline.
- Each injection in a series helping less than the one before.
- Pain that has spread beyond the path of the nerve that was injected.
- Imaging that doesn't match how much pain you're in.
None of these mean the injection was a mistake or that your pain isn't real. They point toward a driver that sits outside the injection's target.
A Failed Injection Is Information, Not a Dead End
When a targeted treatment doesn't produce the expected result, that tells you something about the problem. If reducing inflammation at the nerve root didn't change much, the inflammation at the nerve root probably isn't the whole story.
Even a partial or short-lived result is informative. Relief that lasted a few days suggests inflammation was one contributor among several. Relief that didn't touch the pain at all, or pain that showed up in new places afterward, suggests the signaling system is doing more of the work than the nerve root. Neither outcome is a failure on your part. Both help narrow down what still needs to be addressed.
Too many people hear the opposite message. The injection didn't work, the surgery isn't indicated, the medications haven't done enough, and the conclusion becomes that nothing else can be done. "There's nothing more we can do" is not an evidence-based statement. It usually means the options being considered have all been aimed at the same target.
The standard of care for complex pain is sub-standard care, largely because it keeps looking for one structure to fix. Injections, surgery, and many physical therapy programs share that assumption: find the irritated tissue, treat it, and the pain resolves. That works for many acute problems. It explains far less when pain has become persistent and the signaling system itself has changed.
What This Means for Your Next Step
I'm not telling you to stop injections or to avoid them. That decision belongs to you and your physician, and for some people an injection is a useful tool for getting through a difficult stretch.
The problem is relying on an injection to do something it wasn't designed to do. When relief is temporary, it turns into maintenance: another appointment, another short window, another return to baseline. Real progress comes from addressing the part of the problem the injection can't reach.
It's worth bringing a few direct questions to your next appointment. What exactly was this injection targeting? What does it suggest that it didn't help, or didn't last? Could the way my nervous system processes pain be part of what's happening? Knowing how to talk to your doctor about these questions makes the conversation far more productive.
Neurologic sensitivity can be addressed directly. Pain neuroscience education, graded motor imagery, sensory discrimination, and neurodynamic techniques each target a different part of how the signaling system is processing input. Used in the right order and at the right dose, they work on the amplification itself, which is exactly the piece an anti-inflammatory injection leaves untouched.
A failed injection points you toward the next door. Walk through it.
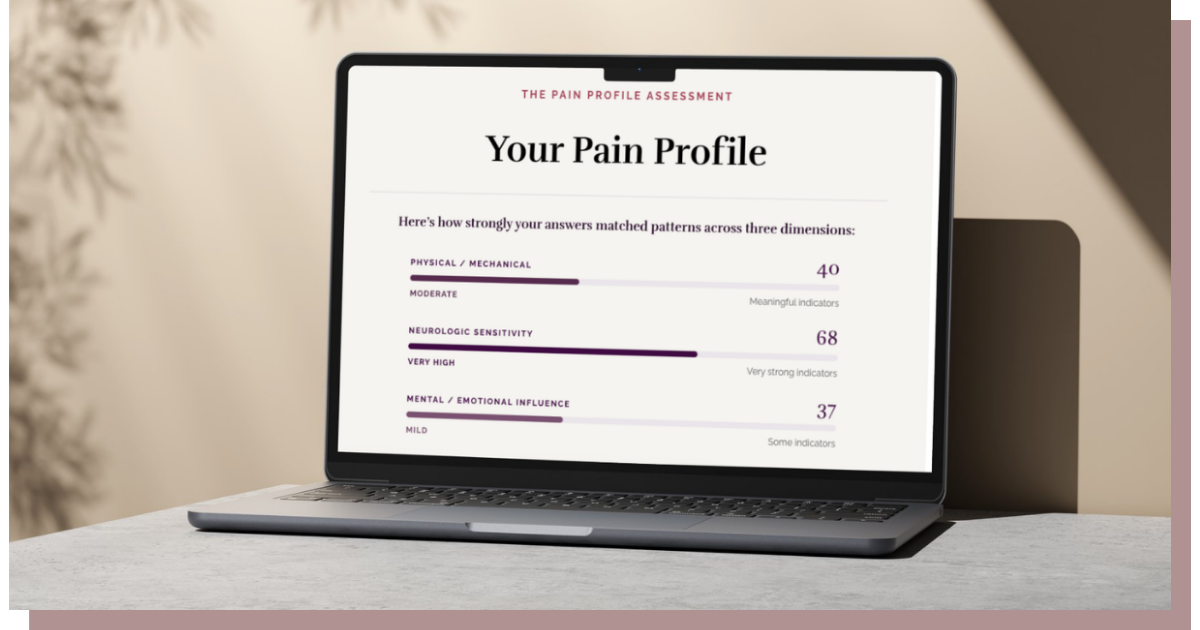
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.