Pain After Knee Replacement 2 Years Later: Why It Persists and Why It Can Still Change
If your knee still hurts two years after a replacement and your surgeon says the implant looks good, the pain is often coming from the signaling system around the knee rather than from the new joint itself. A knee replacement replaces worn joint surfaces. It doesn't reset the pain pathways that spent years adapting before surgery, and those pathways can still change, even years later.
One important step comes first. Persistent pain after a knee replacement deserves a thorough check with your surgeon to rule out surgical complications such as infection, loosening, instability, or a mechanical problem with the implant. If those have been ruled out and you've been told the surgery was a technical success, keep reading. This article is for you.
What a Knee Replacement Fixes, and What It Doesn't
A knee replacement removes damaged cartilage and bone and replaces those surfaces with an implant. It addresses the structure. When it goes well, the X-ray looks excellent, the alignment is good, and the mechanical problem that existed before surgery is gone.
What it doesn't address is everything the nervous system learned during the years you lived with a painful knee:
- Pain pathways that have become more responsive and more easily activated.
- A blurred, or smudged, representation of the knee in the brain.
- Protective guarding: muscles that brace, movements that shorten, a joint that's held stiff.
- Amplifiers like poor sleep, stress, and fear of movement that keep sensitivity high.
That's why a surgery can be a technical success and still leave you in pain. The procedure did its job. The remaining pain has a different driver.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
Years of Pain Before Surgery Leave a Mark
Very few people go straight from a healthy knee to a replacement. Most live with knee pain for years first, often managing it with every option available until surgery becomes the next step.
During those years, the signaling system adapts. The nerves and pathways that carry and process pain signals become more responsive, react to more things, and stay activated longer than they used to. That's neurologic sensitivity, and it doesn't disappear when the original source of pain is removed. Understanding the long-term effects of pain on the nervous system explains a lot about why the knee can keep hurting after the structure has been fixed.
Phantom limb pain is the clearest example of this principle. When someone loses a leg, the brain's representation of that leg is still there, and the pathways that served it can keep firing without any input from the limb at all. The structure is gone. The signaling continues.
A replaced knee is a far less dramatic version of the same idea. The worn surfaces are gone. The pathways that spent years responding to them are still active.
There's also the map. Your brain keeps a detailed representation of each body part. After long periods of pain and reduced use, that representation can become smudged: less precise, less clear. A smudged map can contribute to pain, stiffness, a knee that feels unfamiliar or not quite yours, and movement that never feels natural, even when the joint is mechanically sound.
Protective Guarding Keeps the Cycle Running
After years of pain and a major surgery, your body learns to protect the knee. Muscles around it brace. You shorten your stride, avoid bending it fully, shift weight to the other leg, and move cautiously on stairs.
That protective response makes sense early in recovery. Over time, it keeps the system on alert. Guarding creates stiffness and altered movement, which create more input, which feeds the sensitivity, which reinforces the guarding.
Guarding also changes the information your brain receives from the knee. A joint that's always braced and moved through a narrow range sends a limited, repetitive stream of input. The map gets less detail to work with, and the system has fewer chances to register ordinary movement as safe. Over months and years, that narrow input becomes part of what keeps sensitivity high.
Pushing harder through rehab rarely breaks this cycle. Forcing range of motion or strength work through significant pain tells the protective system it was right to be on alert. The principle I teach is push to it, not through it: work up to the edge of what your system currently tolerates rather than forcing past it.
Why It Can Still Change at Two Years, or Five
At some point after a knee replacement, many people hear some version of "this is as good as it gets." Recovery has plateaued. The knee looks fine. There's nothing left to fix.
"There's nothing more we can do" is not an evidence-based statement. It means there's nothing more to do structurally. The signaling system is a different matter. Your nervous system stays adaptable throughout life, which means the sensitivity that developed over years of pain can also come down.
Addressing it looks different from standard post-surgical rehab. Pain neuroscience education builds an accurate understanding of what's driving the pain, which on its own reduces threat. Graded motor imagery and sensory discrimination work on sharpening the brain's map of the knee. Neurodynamic techniques address nerves that have become sensitive to movement. Strengthening still matters, and it works far better once sensitivity has settled enough for the work to be tolerable and consistent.
Most programs start with strengthening. That's exactly why they stall. Order and dose decide whether these approaches help or flare you, and that's what a structured plan provides.
Your surgeon fixed the structure. The next step is addressing the signaling system that the surgery was never designed to reach.
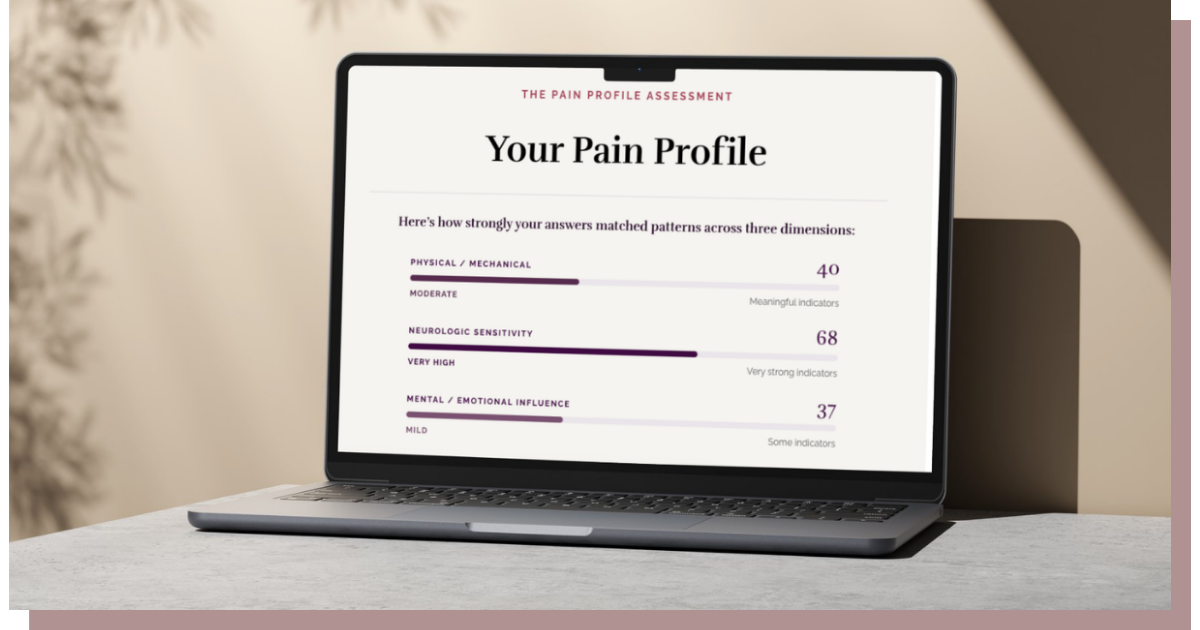
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.