What to Do When Pain Management Doesn't Work: The Missing Layer of Care
If pain management hasn't worked for you, the next step is not another version of the same thing. Medications, injections, nerve blocks, and procedures are designed to quiet the pain signal. They don't change why the signaling system became so sensitive in the first place, and when that sensitivity is what's driving your pain, you need a different layer of care.
That layer works on the system producing the signal. Most people with persistent pain have never been offered it, and that gap explains a lot of "nothing has worked."
What Pain Management Is Built to Do
Pain management physicians are skilled at what they do. Their tools reduce the intensity of pain signals. Some medications change how nerves fire or how the brain registers incoming signals. Injections target inflammation or numb a specific nerve. Procedures interrupt a pathway. When pain comes from an injured or inflamed structure, those tools can be exactly what's needed. In a severe flare, they can make the next step possible.
The trouble shows up when the relief keeps wearing off. You get a great week after an injection, then you're back where you started. A medication takes the edge off for a few months, then needs adjusting. Every round becomes maintenance, and maintenance is draining: physically, mentally, and financially.
Over time, the cycle of appointments, late-night searching, and the next thing to try starts to feel like chasing your tail. That's usually when people start asking what else is out there.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
Why the Relief Keeps Wearing Off
With persistent pain, the signaling system itself adapts. The pathways that detect and transmit danger signals become overactive. They respond to less input, respond more strongly, and stay active longer. I call this neurologic sensitivity.
Think of a smoke detector that goes off every time you take a hot shower. You can pull the batteries and the house goes quiet. Put them back in, and the detector is exactly as sensitive as it was before. Quieting the alarm didn't change how easily it sounds.
Standard pain management works on the alarm. Neurologic sensitivity lives in the detector. That's why the effect fades, and why the next treatment often fades the same way.
Amplifiers add to the problem. Poor sleep, ongoing stress, fear of movement, swinging between doing too much and doing too little: each one pushes the system's sensitivity higher while a treatment is trying to bring the signal down.
None of this shows up on an MRI. It doesn't show up on a nerve conduction study either. Overactive nerves, changes in how the brain processes sensation, and pain responses that have become automatic are invisible to the tests most care plans are built around. When the plan is built only on what the scan shows, something is being missed.
"There's Nothing More We Can Do" Is Not an Evidence-Based Statement
At some point, many people hear a version of this: you've tried the medications, the injections, and the procedure, so there's nothing more we can do.
What that usually means is that there's nothing more within that toolkit. It's an honest description of one specialty's limits. It says nothing about your nervous system's capacity to change.
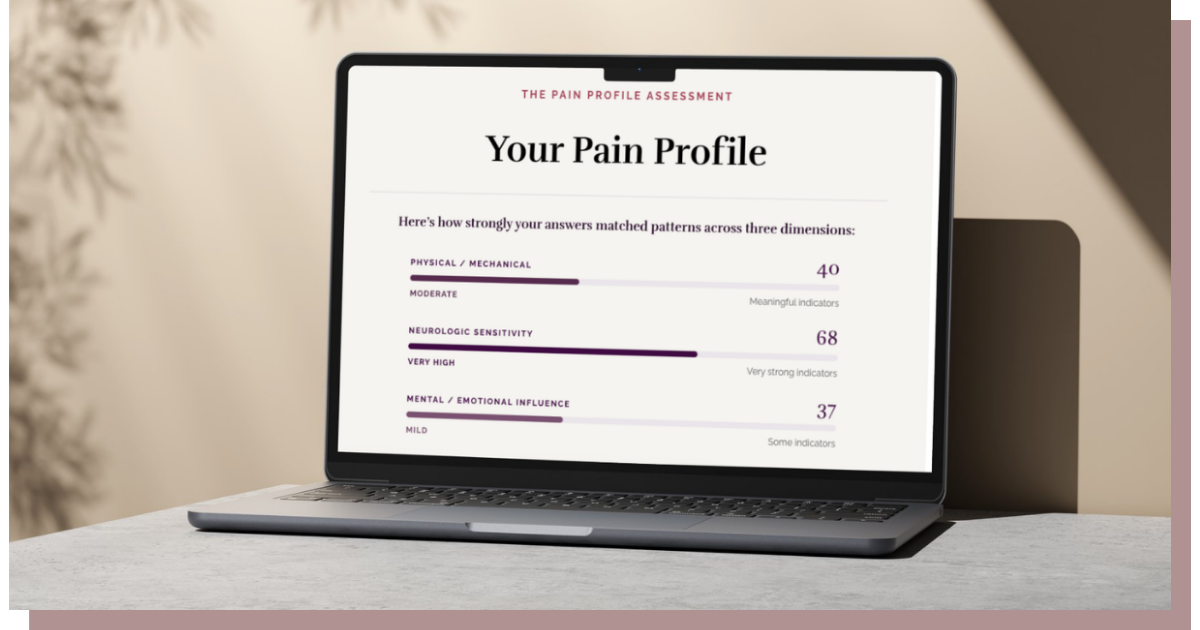
Persistent pain has more than one dimension. There's the physical piece, the neurologic sensitivity piece, and the mental and emotional piece. Pain management addresses part of one of them. Most clinicians were trained to find and fix a damaged structure, and very few were trained to treat a sensitized signaling system. That's a gap in training, and it's no reason to stop.
The standard of care for complex pain is sub-standard care. No single doctor created that problem. The system simply wasn't built for this kind of pain.
What a Different Layer of Care Looks Like
The missing layer targets the sensitivity itself. It treats the signaling system as something that can adapt in both directions, because it can. The same adaptability that let it become more sensitive lets it become less sensitive.
In practice, that layer is a strategic integration of evidence-based methods:
- Pain neuroscience education, so you understand what your system is doing and fear has less to work with.
- Sensory discrimination and graded motor imagery, which target the brain's body maps when they've blurred.
- Neurodynamic techniques aimed at nerves that have become overactive.
- Pacing adapted for sensitivity. Push to it, not through it.
- Progressive strengthening, once sensitivity has started to settle.
- Flare prevention built on knowing your amplifiers.
Order and dose decide whether these methods help or flare you. Most programs start with strengthening. That's exactly why they stall. A sensitized system needs the sensitivity addressed first, at a dose it can tolerate, before load is added.
This layer doesn't replace your medical care. Medications and injections can still have a place. The goal is to use them because you choose to, not to rely on them day in and day out just to get through. Any change to your medications belongs in a conversation with your prescribing doctor.
What to Do When Pain Management Isn't Working
Start by recognizing the pattern. If your relief keeps fading, and each new treatment works on the same mechanism as the last one, trying harder in the same direction will produce the same result.
Then change the question. Instead of "what else can quiet this?", ask "what is keeping my system this sensitive?" That question opens a different set of answers.
Bring it to your care team. Ask whether a proposed treatment is meant to quiet the signal or change the sensitivity behind it, and what the plan is once the effect wears off. If you want help framing that conversation, my guide on how to talk to your doctor about chronic pain walks through it.
If you've developed new or different symptoms, talk to your doctor to rule out other causes before assuming it's the same pain. And if the workup is clear and the relief still won't last, the road doesn't end there. The neurologic layer simply hasn't been addressed yet.
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.