Does Perimenopause Make Fibromyalgia Worse? How Hormone Shifts Amplify Pain
Yes, perimenopause can make fibromyalgia worse. Many women notice their fibromyalgia, joint pain, or widespread pain change during perimenopause and menopause. Hormone shifts don't cause fibromyalgia, but they can act as an amplifier on a signaling system that's already sensitive, and that distinction changes what you can do about it.
If your pain has shifted in your forties or fifties and you've been told "that's just your fibro" or "that's just menopause," you deserve a better explanation than a label. Here it is.
Hormones Are an Amplifier, Not the Cause
Fibromyalgia and many other forms of persistent pain share a common layer underneath: neurologic sensitivity. The nerves and pathways that carry and process pain signals have become more responsive, react to more things, and stay activated longer than they used to. Pain shows up more easily, spreads more widely, and lingers.
A sensitive system responds to amplifiers. Amplifiers are anything that raises sensitivity in a system that's already primed: poor sleep, stress, illness, overexertion, weather changes, and hormonal shifts. They don't create the underlying sensitivity. They push it higher. Protectors do the opposite, lowering the overall load on the system.
During perimenopause, estrogen and progesterone fluctuate before they decline. Estrogen interacts with the way the nervous system processes pain signals, so when it swings, the system's sensitivity can swing with it. Perimenopause also tends to bring indirect amplifiers along: night sweats that fragment sleep, shifts in mood, more fatigue, more stress. Each one adds load.
For a system that was holding steady, that combination can be enough to push sensitivity past what you were used to managing. That's why women who managed their fibromyalgia well for years sometimes find it harder to manage in midlife, and why some women develop widespread pain for the first time in this season.
For complex and persistent pain
Something is being missed.
The Uprising: Complex Pain Academy is a structured, 5-phase program that targets the neurologic sensitivity behind persistent pain, in the right order and at the right dose, with a specialist guiding every step.
How Pain Can Change During Perimenopause and Menopause
The changes aren't the same for everyone, but some patterns come up again and again:
- Fibromyalgia flares that feel more frequent or less predictable.
- Joint aches in the hands, hips, knees, or shoulders that seem to come from nowhere.
- Pain that moves around the body or covers a wider area than before.
- More sensitivity to touch, pressure, or temperature.
- Fatigue and brain fog that make pain harder to manage.
The unpredictability is often the hardest part. Hormone fluctuations during perimenopause are uneven, so the amplifier is uneven, and pain can feel random. It isn't. Flares follow amplifiers, even when the amplifier is hard to see.
It also helps to know that amplifiers stack. A night of fragmented sleep on its own might not change much. Fragmented sleep plus a stressful week plus a hormonal swing can add up to a flare that seems out of proportion to any single cause. Seeing the stack, instead of searching for one culprit, is what turns random-feeling pain into something you can understand and plan around. It's also why chasing a single fix for perimenopausal pain so often disappoints: the load is coming from several directions at once.
Not every new symptom in midlife is hormonal, and not every new pain belongs to fibromyalgia. Talk to your doctor to rule out other causes, especially for pain that's new, localized, or different in character from what you usually feel.
"That's Just Your Fibro" and "That's Just Menopause" Aren't Answers
Once a woman has a fibromyalgia diagnosis in her chart, it's remarkable how often every new symptom gets attributed to it. Add perimenopause, and the explanations narrow even further. Fibro. Menopause. Hormones. Age.
These labels often close the file instead of opening a treatment plan. They're labels with no instructions, and they reveal a real gap in how complex pain is handled: the inability to address complex issues with practical strategies.
Asking why something is happening doesn't make you difficult. Understanding the why reduces fear and uncertainty, which in many cases reduces symptoms too, and it points you toward more effective action. If your concerns keep getting waved away, it helps to know how to talk to your doctor in a way that gets you a real conversation.
What You Can Influence Right Now
Decisions about hormones belong between you and your physician. That's outside my lane and outside the scope of this article.
What you can influence, regardless of where you are in the transition, is the sensitivity underneath. Think of it as a set point. When the set point is high, every amplifier, hormonal or otherwise, has a lot to work with. When the set point comes down, the same amplifier produces a smaller response. You don't have to wait for your hormones to settle to start lowering it.
That's the work that changes the picture. Pain neuroscience education builds an accurate understanding of what's driving your pain. Graded motor imagery, sensory discrimination, and neurodynamic techniques target how the signaling system is processing input. Pacing adapted for a sensitive system lets you build activity without feeding flares. Strengthening comes in once sensitivity settles enough for it to be consistent.
Order and dose decide whether these approaches help or flare you, and that's what a structured plan provides.
Midlife is often when women decide they're done accepting vague answers about their bodies. That's a strong place to start from. Perimenopause can amplify pain. It doesn't get to decide where your pain goes from here.
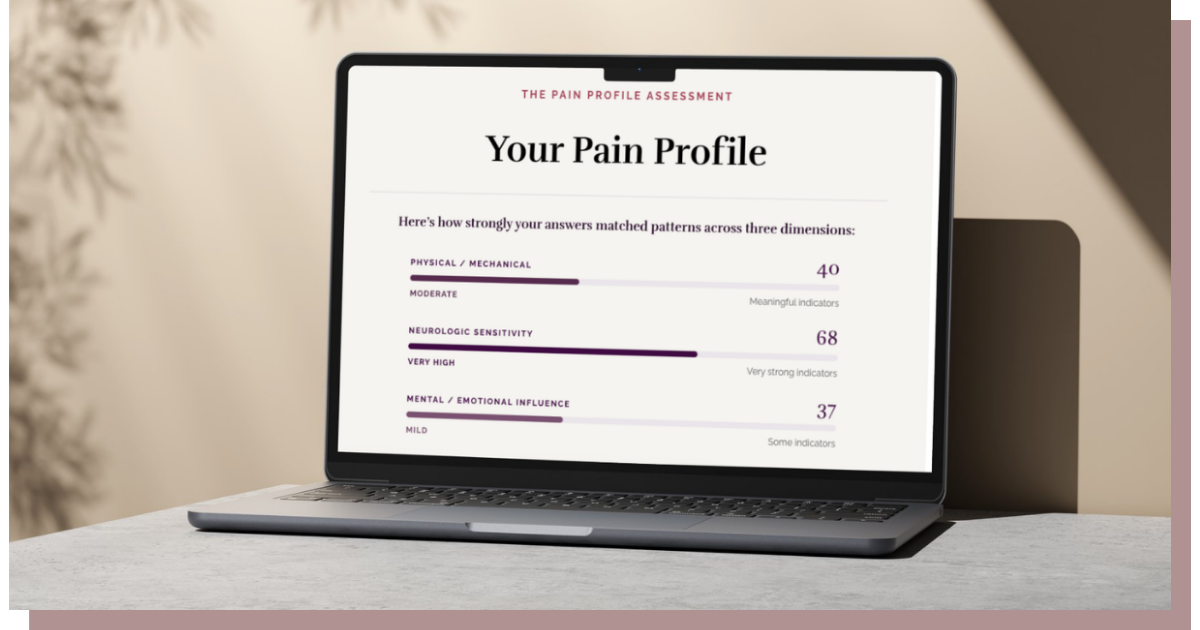
Not sure which dimension is driving your pain? Take the free Pain Profile quiz and get three separate scores: physical, neurologic sensitivity, and mental/emotional.
If neurologic sensitivity turns out to be the driver, that's exactly what The Uprising: Complex Pain Academy is built to address.